“Mommy Pouch” or Medical Condition? What Your Postpartum Tummy Is Really Telling You
By Alexis Lee
, Women’s Health Physiotherapist at Plan V
Struggle with a post-pregnancy "mommy pouch" and lower back pain? Learn how specialized women's health physiotherapy helps heal Diastasis Recti safely.
What Is the “Mommy Tummy,” Really?
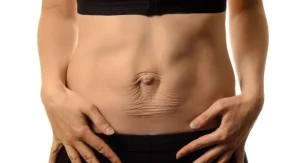
The soft, forward-protruding abdomen many women notice after pregnancy is commonly called the mommy pouch or mommy tummy(Figure 1). Most women assume it is simply leftover fat or stretched skin. Sometimes it is. But frequently, the persistent pouch — particularly one that appears as a ridge or dome down the midline during exertion — signals something more specific: diastasis recti abdominis (DRA).
Figure 1: Diastasis Recti
During pregnancy, the growing uterus stretches the linea alba — the connective tissue band running vertically down the midline that joins the two rectus abdominis (“six-pack”) muscles. This widens the gap between the muscle bellies, and the abdomen loses its structural integrity at the centre. Postnatally, this gap — the inter-recti distance (IRD) — should narrow and the linea alba should regain tension(Figure 2). In a significant proportion of women, it does not.
Figure 2: Difference of Normal Abdomen & Diastasis Recti
Prevalence estimates suggest DRA affects up to 39% of women at six months postpartum and around 32% at twelve months — far more common than most postnatal care pathways acknowledge. The mommy pouch that “won’t go away no matter what I do” is often this condition, and no amount of sit-ups will fix it. In fact, sit-ups make it worse.
Why DRA Causes Low Back Pain
This is where many women — and clinicians — miss the connection.
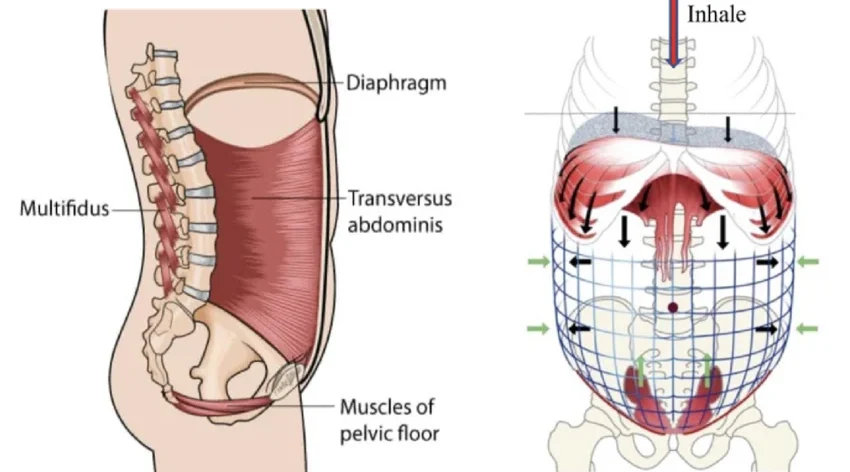
The linea alba is not passive connective tissue. It is a force transmission structure. The deep abdominal muscles, particularly the transversus abdominis (TrA), generate tension that crosses the midline through the linea alba to stabilise the lumbopelvic region(Figure 3). This is part of a coordinated deep stabilising system that also includes the pelvic floor, diaphragm, and deep spinal muscles — working together to protect the spine during all movement and loading.
When the linea alba loses tensile capacity, this system breaks down. Forces that should be transmitted across the midline instead dissipate. The spine is left without adequate dynamic support, and load falls on structures — facet joints, sacroiliac ligaments, intervertebral discs — not designed to bear it chronically.
The result is low back pain: often central or bilateral, worse with lifting, prolonged standing, transitioning from lying to sitting, and the repetitive asymmetric demands of caring for a newborn and a toddler simultaneously.
Critically, research by Lee & Hodges (2016) established that it is not the width of the IRD alone that drives dysfunction — it is the ability of the linea alba to generate tension under load. A wide gap with preserved tension may cause minimal symptoms. A moderate gap with poor tissue tension can produce significant lumbopelvic instability and pain. This is why measuring the gap with a tape measure tells only part of the story.
Meet Aishah
Aishah, 34, a teacher and mother of two, walked into my clinic four months after her second delivery — one hand on her lower back, the other holding her baby.
“I know the mommy pouch is normal after having kids,” she said. “But my back hasn’t stopped hurting, and my tummy still feels like it belongs to someone else.”
She had been cleared for exercise at her six-week check. She had been doing sit-ups at home. Her back was getting worse, not better.
What Aishah had been told was a cosmetic inevitability was, in fact, a clinical condition driving her pain. She had diastasis recti abdominis — and nobody had looked for it.
Aishah’s Assessment
On assessment, Aishah’s IRD measured 3 fingers gap at the umbilicus. More significantly, when asked to perform a head lift from supine, visible midline doming occurred immediately — the linea alba offered negligible resistance under load. This is the clinical hallmark of DRA with poor tissue function.
Further findings included:
Absent feedforward TrA activation — her deep stabilising system had effectively switched off, replaced by a dominant superficial bracing strategy using the rectus abdominis and erector spinae
Pelvic floor hypotonicity with poor coordination alongside breath and deep abdominal muscles
Upper chest breathing pattern and breath-holding during exertion — further disrupting IAP regulation
She had been doing sit-ups for six weeks. Sit-ups maximally recruit the rectus abdominis, forcefully increasing IAP and driving it through the weakest point — the midline. She had been loading a structurally compromised system with exactly the wrong exercise.
Treatment: What Actually Works
Aishah’s rehabilitation followed three progressive phases over sixteen weeks.
Phase 1 (Weeks 1–4) focused on restoring the foundations: diaphragmatic breathing mechanics, isolated deep TrA activation (confirmed with real-time ultrasound biofeedback), pelvic floor recruitment, and activity modification. In the early phase, manual therapy also targets the fascial restrictions and myofascial tension that develop around the linea alba and lateral abdominal wall following pregnancy.
Phase 2 (Weeks 5–10) introduced progressive lumbopelvic loading: dead bug variations, bridging progressions, Pallof press (anti-rotation band work loading the lateral abdominal wall without midline compression), and modified side planks(Figure 4). These exercises target the muscles that provide lateral tension to the linea alba — rebuilding the connective tissue’s functional environment — without generating the midline strain of traditional core exercises.
Figure 4: Diastasis Recti Exercises Physiotherapy
By week eight, Aishah’s back pain had reduced from 5–6/10 to 1–2/10 on exertion, and zero at rest. Ultrasound confirmed improved TrA recruitment. Midline doming on the head lift test had resolved. Her IRD remained at 1 Finger — her linea alba was now generating meaningful tension under load.
This is the key clinical point: the gap does not need to fully close for function and pain to resolve.
Phase 3 (Weeks 11–16) progressed to return-to-impact activity, using validated criteria before jogging was reintroduced. At sixteen weeks, Aishah was running, lifting her children, and teaching full days — pain-free.
She still had a mommy pouch. But it no longer domed under load, and it no longer hurt.
The Missed Opportunity: Postnatal Screening
Aishah was not screened for DRA at her six-week postnatal check. This is the norm, not the exception — in Malaysia and globally. Women receive clearance for exercise based on time, not function. They are told the mommy tummy is cosmetic. They go home and do sit-ups.
A brief postnatal screen — assessing IRD, linea alba tension under load, and lumbopelvic function — combined with a low threshold for physiotherapy referral, would identify women like Aishah early, during the window when tissue remodelling and neuromuscular re-education are most responsive. Instead, many arrive months or years later with entrenched dysfunction and the belief that their bodies simply did not recover.
They did not fail to recover. They were not given the tools to.
What to Watch For
Speak to a women’s health physiotherapist if you notice, postnatally:
Visible ridging or doming along the midline during sit-ups, coughing, or rising from bed
A persistent mommy pouch that feels soft and unsupported rather than firm
Low back or sacroiliac pain that began or worsened after delivery
A feeling that your core “does nothing” even when you try to engage it
Urinary leakage — pelvic floor and DRA dysfunction frequently coexist
Conclusion
The mommy pouch is not always just a cosmetic concern, and low back pain after having children is not something you simply have to accept. When the two occur together, diastasis recti is a likely and treatable contributor — but only if someone looks for it.
Physiotherapy assessment and rehabilitation, when applied correctly, produces excellent outcomes. The gap in care is not in the evidence. It is in the screening, the conversation, and the referral.
If your postpartum body does not feel like yours yet — it may be waiting for the right support, not more sit-ups.
References: Lee D & Hodges PW (2016), JOSPT. Groom, Donnelly & Brockwell (2019), JPOGP. Written from clinical practice in women’s health physiotherapy, Malaysia
At Plan V, you can take that step directly. You don’t need a referral, and you don’t need to have it all figured out first, just a private, judgment-free conversation with an all-female team, whenever you’re ready.
Why are sit-ups making my back pain and "mommy pouch" worse?
Traditional sit-ups push abdominal pressure directly against your weakened midline (linea alba). If you have Diastasis Recti (DRA), this worsens the midline bulge and strains your back instead of strengthening your core.
I was cleared at my 6-week check. Doesn't that mean my core is fine?
Standard 6-week checks confirm wound healing and uterine recovery, not core function. Clearance is time-based, so a functional assessment by a specialized physiotherapist is still recommended before intense workouts.
I still have a 1–2 finger gap. Is my core recovery a failure?
No. Tissue tension is far more important than gap width. If your midline can support load without bulging or causing back pain, your core is functional—even with a small gap.
Can Diastasis Recti cause pelvic floor issues like leakage?
es. Your deep abdominals, pelvic floor, and diaphragm work as one connected team. When DRA disrupts abdominal tension, pelvic floor symptoms like leakage or heavy pressure often follow.
Is it too late to treat DRA if I gave birth months or years ago?
It is never too late. With targeted deep-core activation and progressive loading, you can restore core strength and relieve back pain even years after delivery.
Is pain during sex after pregnancy holding you back? Kegels may not help if your pelvic floor is too tight. Learn how pelvic physiotherapy and relaxation techniques can relieve post-partum discomfort.